Two days at the Kensington Conference and Events Center in London. Roughly 200 delegates and 25 speakers from across the digital health ecosystem – providers, payers, life sciences companies, and the vendors building the infrastructure underneath all three. The Digital Health World Congress is one of the more concentrated rooms in European health tech: fewer keynote stages than at a mega-conference, more conversations that go deep into a single implementation problem before moving on to the next.
Our COO, Andrew Yakibchuk, attended DHWC 2026 in London in May. What he came back with was a pattern, and it’s a familiar one to anyone who has tried to move a healthcare AI system from a working demo into a production environment.

Digital health has reached a specific inflection point: whether to invest in AI is no longer the debate. The debate is how to get a system from pilot to regulated, patient-facing production without breaking compliance, clinician trust, or the budget. That’s the signal DHWC 2026 made concrete. What follows is what the agenda covered, what the pattern means, and where we see the clearest engineering opportunities.
Den här artikeln sammanfattar de centrala teman från Digital Health World Congress 2026, såsom AI inom life science, hantering av kroniska sjukdomar, interoperabilitet för hälsodata, ansvarsfull AI och regelefterlevnad, samt övergången från pilotprojekt till reglerad driftsättning, och beskriver de tydligaste tekniska möjligheterna för vårdorganisationer som bygger produktionsklar AI.
- Interoperability determines what AI can actually do: Shared care records and standards-based data exchange are the preconditions for any AI use case that spans more than one system or care setting.
- Regulated AI requires provable quality, not post-hoc documentation: Moving from pilot to regulated scale means building compliance and explainability into the architecture from day one, not adding them before an audit.
- Chronic disease management is where patient-facing AI is furthest along: Continuous monitoring and digital therapeutics are ahead of acute-care AI in real-world deployment maturity.
- Trust between clinicians and AI outputs remains the adoption bottleneck: Even validated models see limited use when their outputs aren’t embedded in the clinical workflow that the care team already trusts.
Inuti DHWC 2026-agendan: Fem trender som definierar digital hälsa
DHWC 2026-programmet pågick över keynote-scener, en panel om marknadsutsikter och en serie kortare, implementeringsfokuserade sessioner under två dagar. Fem teman löpte genom nästan allt:
1. AI accelererar värdekedjan inom life science
Several sessions framed AI’s impact on discovery-to-market timelines as a compression problem: the stages between a molecule and a marketed therapy are shortening as AI takes on more of the analytical load, from trial design to real-world evidence generation. Strategy-focused talks addressed the same shift from a different angle, looking at how life sciences organizations sequence AI investment against innovation priorities that are still evolving. The throughline: AI in life sciences is delivering its biggest wins earlier in the pipeline than most non-specialists expect.
2. Patientengagemang: AI och hantering av kroniska sjukdomar hamnar i rampljuset
Some of the most concrete patient-facing sessions on the agenda addressed managing chronic disease with digital health – continuous monitoring, remote patient data, and intervention models built around conditions that unfold over months and years rather than single encounters. Other sessions on personalizing wellness to biometrics and on body composition tracking in a GLP-1-driven market extended the same theme: AI-powered patient engagement is maturing fastest where the data stream is continuous, and the intervention window is long — a pattern that’s reshaping chronic disease management technology across the board.

3. Interoperability and Shared Care Records as Healthcare’s Connective Tissue
Öppningstalet — att överbrygga dataklyftan mellan industriella datamodeller och patientvård — satte en ovanlig men användbar ram: interoperabilitet inom sjukvården ser strukturellt sett liknande ut som problem som redan lösts inom industriell IoT, bara med en mycket högre efterlevnadströskel. En session om digital infrastruktur för delade vårdjournaler tog upp samma problem från den kliniska sidan: vad som faktiskt krävs för att ge ett vårdteam en sammanhängande journal när de underliggande systemen aldrig utformats för att dela en. IoT-fallstudier från området uppkopplad hälsa rundade av detta tema från enhetssidan.
“The quality of the conversation at DHWC this year was different – almost nobody was still asking whether AI belongs in healthcare. They were asking how to get it through compliance, into the clinical workflow, and in front of a clinician who’d actually trust it.” — Andrew Yakibchuk, COO, Crunch-IS
4. Ansvarsfull, säker AI för reglerade vårdmiljöer
Ett av de tydligaste uttalandena på DHWC 2026 argumenterade för att efterlevnad-som-kryssruta inte längre är en trovärdig position för AI-leverantörer inom hälsovården. En session om ansvarsfull AI inom sjukvård och medicinskt beslutsfattande gick igenom en europeisk fallstudie om samma problem: hur man gör HIPAA-kompatibel AI och AI-stödda kliniska beslut försvarbara, inte bara korrekta. En separat session om kvantberedskap för cybersäkerhet inom hälsovården signalerade att planeringshorisonterna för säkerhet sträcker sig långt bortom nuvarande hotmodeller.
5. Övergång från pilotprojekt till reglerad, skalbar driftsättning
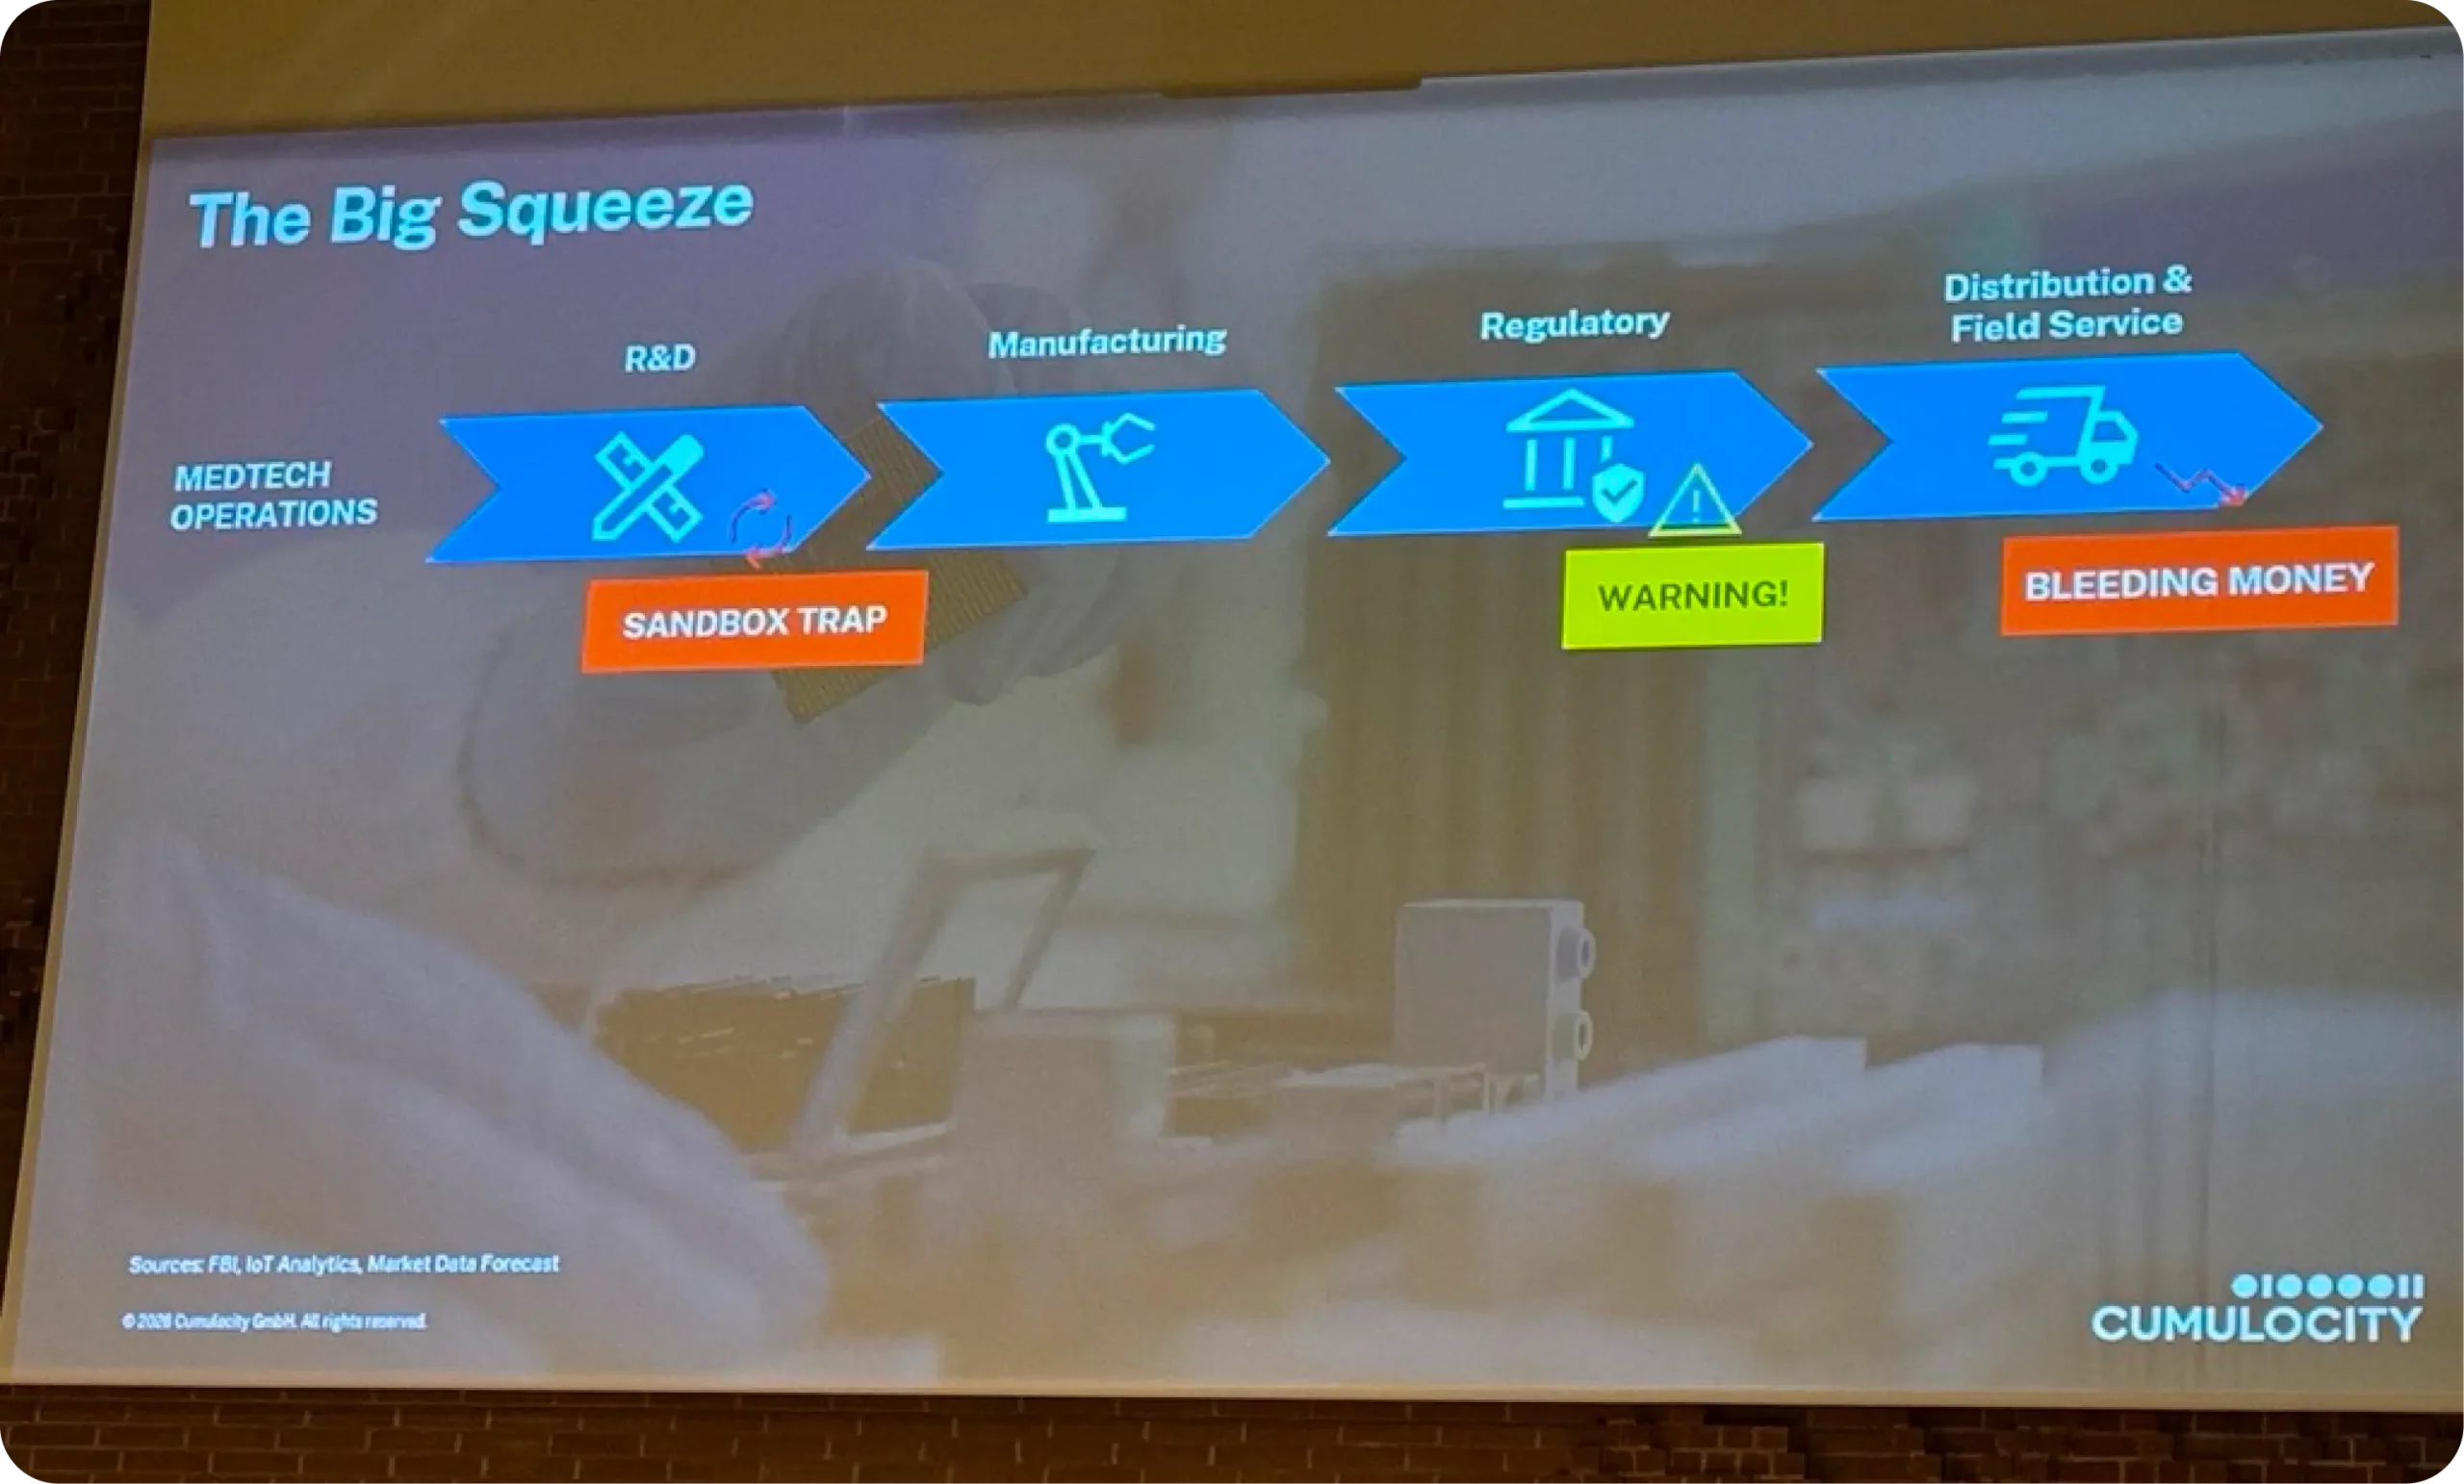
One session, addressing the move from AI pilots to regulated scale directly, tackled the gap this article keeps coming back to: the distance between a working pilot and a regulated AI deployment cleared for patient-facing use. Other sessions on digital inclusion — making sure AI-driven care models don’t leave patients without reliable connectivity or digital literacy behind — and on the evolution of digital health from apps to community-driven models rounded out a program that spent as much time on adoption and equity as it did on model performance.
Bortom sessionerna: Var införandet av AI inom sjukvården verkligen står
DHWC 2026 confirmed three gaps between where most healthcare organizations are with AI and where they need to be. Each requires a different kind of engineering to close, and each shows up repeatedly in Crunch-IS’s own healthcare engagements.
Att överbrygga klyftan i beredskap för kliniska data
Clinical data is not clean tabular data. It’s structured EHR fields, free-text physician notes, imaging studies, wearable telemetry, and legacy exports, governed by HIPAA and, in the UK and EU contexts, NHS and GDPR requirements. Getting from that state to a model-ready dataset means mapping to clinical terminology standards — SNOMED CT, LOINC, ICD-10 — building FHIR-compliant data layers, and putting healthcare data governance controls in place before a model ever sees the data. This step is consistently underestimated at the start of digital health programs and rarely underestimated a second time.
Från pilot till reglerad produktion: driftsättningsgapet
Moving from a working pilot to a regulated, production-grade AI system requires MLOps for a healthcare discipline that goes well beyond model accuracy: monitoring for data and model drift, retraining pipelines, audit logging, and — critically in a clinical setting — outputs that are explainable to the clinicians and compliance staff who have to act on them. This is a design constraint built into the architecture from the outset, not documentation added before a review. It’s also where several of DHWC’s pilot-to-scale and compliance-focused talks converged: pilots that work rarely fail on model performance. They stall on the engineering required to operate safely at regulated scale.
Att förtjäna klinikers förtroende för AI-assisterade beslut
The final constraint behind clinical decision support AI adoption is organizational, but it has a technical answer. Clinicians who’ve built judgment through years of direct patient contact don’t extend automatic trust to a model score, and they shouldn’t be expected to. The deployment pattern that works builds a trust loop into the system: AI outputs run alongside clinical judgment, disagreements get logged and reviewed, and the system earns adoption over successive cycles rather than being handed down as a mandate. Organizations that treat this as a change-management afterthought see low adoption even when the underlying model is accurate. The engineering work is in the interface between AI output and clinical decision-making, not in the model alone.
Vart digital hälso-AI-investeringar är på väg härnäst
For the organizations furthest along at DHWC 2026, digital health innovation is a current engineering program with a defined path to regulated deployment — not a future investment category. For organizations earlier in the process, the near-term priority is the same as it’s been for the past two cycles: standards-based interoperability, clinical data governance, and a compliance architecture that’s designed in rather than layered on.
Fyra områden väckte det tydligaste investeringsintresset på DHWC 2026, både i programmet och i samtalen på golvet:
- Generativ AI för klinisk dokumentation och administrativa arbetsflöden
- AI-stödd hantering av kroniska sjukdomar och psykisk hälsa byggd på kontinuerliga patientdata — engagemangslagret bakom vårt eget NHS-integrerad plattform för psykisk hälsa
- Standardsbaserad EHR- och integration av delade vårdjournaler
- Klinisk AI för studiescreening, bildbehandling och videoanalys, konstruerad för förklarbarhet och reglerad driftsättning från början
A shortage of ambition doesn’t hold healthcare AI adoption back. What separates the ones making real progress is data engineering done first, compliance built into architecture rather than bolted on, and a deployment approach that earns clinical trust instead of assuming it.
Slutsats
DHWC 2026 confirmed that digital health’s AI conversation has matured. Vendors and health systems alike are past the question of whether AI belongs in clinical and administrative workflows – the harder, more useful conversation now is how to get a system there safely, on standards-based data, in a form clinicians will actually use. The constraint isn’t ambition or budget. It’s the sequence of engineering work between data that exists today and AI systems that clinical teams trust every day, and the discipline to do that work in the right order.
That sequence — interoperable data infrastructure, compliance-first model development, production deployment, and trust built in at every stage — isn’t complicated to describe. It’s demanding to execute where data governance is strict, patient safety is non-negotiable, and the clinicians who need to trust the system’s outputs weren’t in the room when it was built. The organizations that make real progress over the next two to three years will be the ones working with engineering partners who understand that from the inside.